
Surveys · Ethics and law
Informed Consent in Survey Research
Informed consent is the principle that people should take part in research only after understanding what it involves and agreeing freely. This article explains where the principle comes from, what consent to a survey requires, how consent wording affects participation, and the special questions raised by data linkage, passive data and online surveys.
Survey research depends on the willingness of people to give their time and share information about themselves. Informed consent is the principle that they should do so only after being told what the research involves and agreeing freely, without pressure. It is a cornerstone of research ethics, written into professional codes and, in many countries, into law. For survey researchers it raises practical questions: how much to tell respondents, how to record their agreement, and how to obtain meaningful consent for new forms of data collection such as linking survey answers to records or collecting data passively from smartphones.
Origins of the principle
The modern principle of informed consent grew out of medical research. After the Second World War, the Nuremberg Code set out the requirement that research participants give voluntary consent. The Declaration of Helsinki, first adopted by the World Medical Association in 1964 and revised several times since, developed the principle for medical research (World Medical Association, 2013). In the United States, the Belmont Report identified three principles for research with human participants: respect for persons, beneficence and justice. Respect for persons requires that individuals be treated as autonomous agents, which in practice means informed consent (National Commission for the Protection of Human Subjects of Biomedical and Behavioral Research, 1979). Faden and Beauchamp (1986) traced the history of the idea and set out its philosophical basis in the autonomy of the individual.
These principles now apply to social and market research as well as medical research. In the United States, federal regulations known as the Common Rule govern research funded by the government (U.S. Department of Health and Human Services, 2018). In Canada, the Tri-Council Policy Statement sets out requirements for research involving humans (Canadian Institutes of Health Research et al., 2022). Professional codes for survey research, such as those of AAPOR and ESOMAR, require that participation be voluntary and that respondents be told enough to make an informed decision (American Association for Public Opinion Research, 2021; ESOMAR & International Chamber of Commerce, 2016).
What consent requires
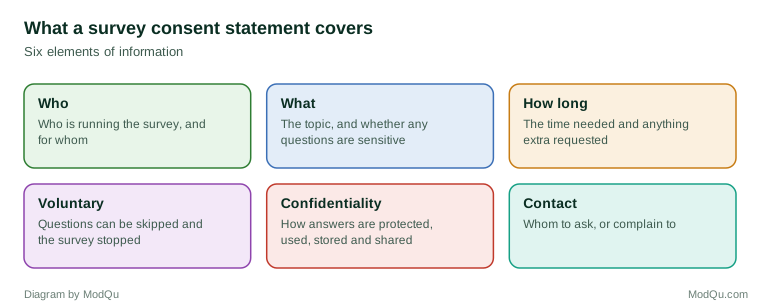
Informed consent has three elements: information, understanding and voluntariness. Respondents must be given the information they need, must understand it, and must agree without coercion. Figure 1 lists the information that consent statements in surveys usually include.
Information
Respondents should be told who is conducting the survey and for whom, what it is about, how long it will take, whether any questions are sensitive, that taking part is voluntary and that they can skip questions or stop at any time, how their answers will be kept confidential, how the data will be used, stored and shared, and whom to contact with questions or complaints. If answers will be linked to other data, or if the survey involves recordings, physical measurements or passive data, respondents must be told so and asked separately.
Understanding
Giving information is not the same as being understood. Long, technical consent forms are often not read. Studies of online consent show that many participants spend only seconds on consent pages and remember little of their content (Varnhagen et al., 2005; Perrault & Nazione, 2016). Outside research, the same pattern applies to online terms of service: in one experiment, most participants agreed to terms that included absurd clauses, such as giving up their first-born child, without noticing (Obar & Oeldorf-Hirsch, 2020). Reviews of efforts to improve understanding in medical research found that discussions with a person and simplified, well-organised documents helped more than longer forms (Flory & Emanuel, 2004; Nishimura et al., 2013).
Voluntariness
Consent must be given freely. Respondents must not be pressured, misled or made to fear consequences if they refuse. Incentives are generally acceptable, but large payments to people in financial need, or surveys run by an employer or a provider of essential services, can make refusal feel risky. In such settings, researchers should take extra care to make clear that refusal will have no consequences and that answers will not be seen by those with power over respondents. Repeated reminders are generally acceptable, but persistent pressure after a clear refusal is not, and interviewers should be trained to recognise and respect a refusal even when it is expressed politely or indirectly. Respondents should also be free to refuse particular questions while answering others, and questionnaires should make it easy to do so, for example by offering a "prefer not to say" option on sensitive items.
How consent is obtained in surveys
Survey research usually uses lighter forms of consent than medical research, reflecting its generally lower risks.
- Implied consent. In many surveys, completing the questionnaire is taken as consent. An introduction explains the survey, and respondents who continue are assumed to agree. This is common in self-completion and online surveys of low risk.
- Verbal consent. In telephone and face-to-face interviews, the interviewer reads a short statement and records that the respondent agreed.
- Written or electronic consent. For more sensitive research, or for additional procedures such as data linkage, respondents sign a form or tick a box.
Ethics committees may also waive the requirement for consent in special cases, such as research using existing data where obtaining consent would be impracticable and the risks are minimal.
Consent in different modes
Each survey mode presents consent differently. In face-to-face interviews, the interviewer can explain the survey, answer questions and judge whether the respondent has understood, and many surveys leave a printed information sheet with the respondent. In telephone interviews, the statement must be short enough to be read aloud without losing the respondent's attention, so key points are given first and further details are offered on request or by post. In postal surveys, a covering letter carries the information, and returning the questionnaire implies consent. In online surveys, consent is usually given on the first screen, often with a tick box or a button labelled to show agreement.
The advance letter sent before many surveys also plays a part. It can explain the purpose of the survey and the protections in place in more detail than an interviewer's introduction, and it gives people time to consider whether to take part before they are approached. A short consent statement at the start of the interview can then refer back to the letter.
Consent and response
A long-standing concern is that detailed consent procedures reduce participation or affect answers. Singer (1978) tested the effects of telling respondents more about the content of a survey and of asking for a signature. Giving more information about sensitive content had little effect on response rates or answers, but asking for a signature before the interview reduced participation. Singer (1993) reviewed later evidence and concluded that most elements of informed consent have little effect on response, except where the request for a signature raises suspicion.
Assurances of confidentiality have a more complex effect. A meta-analysis found that strong assurances slightly increased response to surveys on sensitive topics but could reduce response to surveys on harmless topics, perhaps because elaborate assurances suggest that there is something to worry about (Singer et al., 1995). Couper et al. (2008) found that people's willingness to take part depended on their perceptions of the risk of disclosure and of the harm it would cause, more than on the objective risk. Singer (2003) found that respondents' decisions to participate reflected their beliefs about risks and benefits, and that many did not consider the information in consent statements in detail.
Consent for additional data
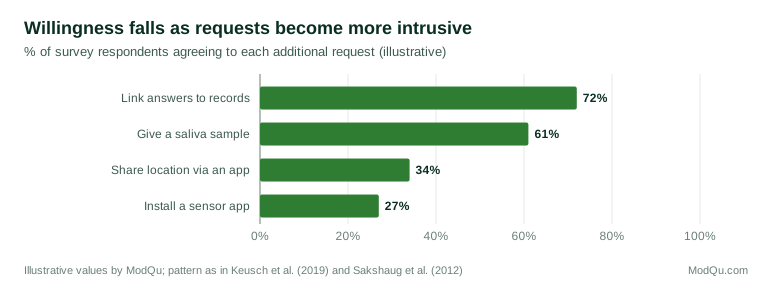
Modern surveys increasingly ask respondents for more than answers to questions. Each additional request needs its own consent, and consent rates vary widely, as Figure 2 illustrates.
Linking survey answers to records
Linking answers to administrative records, such as tax, health or benefit records, can improve data quality and reduce the number of questions asked. In most countries this requires explicit consent. Consent rates vary from below half to over 90 per cent, depending on the survey, the records requested and how the request is made. Studies have identified respondent characteristics associated with consent, such as trust and concerns about privacy, and also features of the interview and interviewer (Sala et al., 2012; Sakshaug et al., 2012). Because those who refuse may differ from those who agree, non-consent can bias analyses that use linked data (Sakshaug & Kreuter, 2012). Where law allows, some surveys use an opt-out approach, in which linkage takes place unless the respondent objects; Das and Couper (2014) studied how such requests can be designed to respect respondents' choices while reducing bias.
Biomarkers and physical measurements
Health surveys may ask respondents to provide blood, saliva or other samples, or to be measured. Each requires separate consent, including consent for storage and any future uses of samples, such as genetic analysis.
Passive and smartphone data
Smartphone apps can collect location, movement, app use and other data continuously. People are much less willing to share such data than to answer questions, and willingness depends on the type of data, who is collecting it and whether they can control what is shared (Keusch et al., 2019). Kreuter et al. (2020) described the challenges of obtaining meaningful consent for such data, including explaining what will be collected and giving participants control, such as the ability to pause collection.
Online surveys and consent
Online surveys make consent easy to obtain but hard to make meaningful. A click-through consent page may satisfy formal requirements without informing anyone. Good practice for online surveys includes:
- Short, layered consent statements, with the key points on the first screen and further details available by link.
- Plain language, avoiding legal and technical terms.
- Clear statements of how long the survey will take and whether any questions are sensitive.
- Separate tick boxes for each additional request, rather than bundling them.
- The ability to withdraw, including how to request deletion of data where possible.
- Easy access to contact details throughout the survey.
Recording and managing consent
Researchers must be able to show what each respondent agreed to. Survey systems should record the date, the version of the consent statement shown and the answer to each consent question, and these records should be kept with the data. When consent wording changes during a study, the version matters: respondents who agreed under an earlier version may not have agreed to a new use.
Consent must also follow the data. If a respondent agreed to the use of their answers for one study but not for sharing with other researchers, the data released to others must exclude their answers or be anonymised so that the restriction no longer applies. Data management plans should state how consent decisions will be applied when data are archived, shared or linked.
Withdrawal
Respondents have the right to stop taking part at any time, and in panel surveys they can leave the panel. Researchers should explain whether data already collected will be kept or deleted if someone withdraws. In many studies, answers already given are kept in anonymised form unless the respondent asks for deletion, and this should be stated in the consent information. Once data have been anonymised or combined in published results, deletion may no longer be possible, which respondents should also be told.
Special situations
Some situations need particular care:
- Children and vulnerable adults, who may not be able to give consent themselves, require consent from a parent or guardian and, where possible, the agreement of the person themselves.
- Covert or deceptive research, in which participants are not told the full purpose of the research, is permitted only in limited circumstances, where it is necessary, the risks are minimal and participants are debriefed afterwards.
- Secondary use of data, where data collected for one purpose are used for another, may require new consent unless the original consent covered such use or the data have been anonymised.
- Recontact, where respondents are invited to take part in later surveys, requires their agreement at the first survey.
Consent and the law
In some places, data protection law sets requirements that overlap with research ethics. Under the European Union's General Data Protection Regulation, consent is one of several possible legal bases for processing personal data, and it must be freely given, specific, informed and unambiguous. Research may also rely on other legal bases, such as tasks in the public interest. Researchers should distinguish between consent as an ethical requirement for participation and consent as a legal basis for processing data, because the two are not always the same.
An example
A university plans an online survey of 3,000 adults about their finances, with an optional request to link answers to tax records. Its first consent page runs to 900 words, and a pilot shows that the median respondent spends 12 seconds on it. The team replaces it with a 120-word summary covering the purpose, time required, voluntary participation, confidentiality and contact details, with a link to full details. The linkage request is moved to the end of the survey, explained in plain language and presented with a separate yes or no question. In the main survey, 68 per cent agree to linkage. A follow-up question shows that most respondents correctly remember that their answers will be linked only if they agreed (illustrative example).
Conclusion
Informed consent rests on respect for the people who take part in research. In surveys, it requires clear information, real understanding and free agreement. Evidence suggests that consent procedures need not harm response, provided they are short, clear and not threatening. New forms of data collection, from record linkage to smartphone sensors, require separate and specific consent and careful attention to whether respondents truly understand what they are agreeing to.
References
American Association for Public Opinion Research. (2021). AAPOR code of professional ethics and practices. AAPOR. https://aapor.org/standards-and-ethics/
Canadian Institutes of Health Research, Natural Sciences and Engineering Research Council of Canada, & Social Sciences and Humanities Research Council of Canada. (2022). Tri-Council policy statement: Ethical conduct for research involving humans – TCPS 2 (2022). Government of Canada.
Couper, M. P., Singer, E., Conrad, F. G., & Groves, R. M. (2008). Risk of disclosure, perceptions of risk, and concerns about privacy and confidentiality as factors in survey participation. Journal of Official Statistics, 24(2), 255–275.
Das, M., & Couper, M. P. (2014). Optimizing opt-out consent for record linkage. Journal of Official Statistics, 30(3), 479–497. https://doi.org/10.2478/jos-2014-0030
ESOMAR & International Chamber of Commerce. (2016). ICC/ESOMAR international code on market, opinion and social research and data analytics. ESOMAR. https://esomar.org/code-and-guidelines/icc-esomar-code
Faden, R. R., & Beauchamp, T. L. (1986). A history and theory of informed consent. Oxford University Press.
Flory, J., & Emanuel, E. (2004). Interventions to improve research participants' understanding in informed consent for research: A systematic review. JAMA, 292(13), 1593–1601. https://doi.org/10.1001/jama.292.13.1593
Keusch, F., Struminskaya, B., Antoun, C., Couper, M. P., & Kreuter, F. (2019). Willingness to participate in passive mobile data collection. Public Opinion Quarterly, 83(S1), 210–235. https://doi.org/10.1093/poq/nfz007
Kreuter, F., Haas, G.-C., Keusch, F., Bähr, S., & Trappmann, M. (2020). Collecting survey and smartphone sensor data with an app: Opportunities and challenges around privacy and informed consent. Social Science Computer Review, 38(5), 533–549. https://doi.org/10.1177/0894439318816389
National Commission for the Protection of Human Subjects of Biomedical and Behavioral Research. (1979). The Belmont report: Ethical principles and guidelines for the protection of human subjects of research. U.S. Department of Health, Education, and Welfare.
Nishimura, A., Carey, J., Erwin, P. J., Tilburt, J. C., Murad, M. H., & McCormick, J. B. (2013). Improving understanding in the research informed consent process: A systematic review of 54 interventions tested in randomized control trials. BMC Medical Ethics, 14, Article 28. https://doi.org/10.1186/1472-6939-14-28
Obar, J. A., & Oeldorf-Hirsch, A. (2020). The biggest lie on the internet: Ignoring the privacy policies and terms of service policies of social networking services. Information, Communication & Society, 23(1), 128–147. https://doi.org/10.1080/1369118X.2018.1486870
Perrault, E. K., & Nazione, S. A. (2016). Informed consent—uninformed participants: Shortcomings of online social science consent forms and recommendations for improvement. Journal of Empirical Research on Human Research Ethics, 11(3), 274–280. https://doi.org/10.1177/1556264616654610
Sakshaug, J. W., & Kreuter, F. (2012). Assessing the magnitude of non-consent biases in linked survey and administrative data. Survey Research Methods, 6(2), 113–122. https://doi.org/10.18148/srm/2012.v6i2.5094
Sakshaug, J. W., Couper, M. P., Ofstedal, M. B., & Weir, D. R. (2012). Linking survey and administrative records: Mechanisms of consent. Sociological Methods & Research, 41(4), 535–569. https://doi.org/10.1177/0049124112460381
Sala, E., Burton, J., & Knies, G. (2012). Correlates of obtaining informed consent to data linkage: Respondent, interview, and interviewer characteristics. Sociological Methods & Research, 41(3), 414–439. https://doi.org/10.1177/0049124112457330
Singer, E. (1978). Informed consent: Consequences for response rate and response quality in social surveys. American Sociological Review, 43(2), 144–162. https://doi.org/10.2307/2094696
Singer, E. (1993). Informed consent and survey response: A summary of the empirical literature. Journal of Official Statistics, 9(2), 361–375.
Singer, E. (2003). Exploring the meaning of consent: Participation in research and beliefs about risks and benefits. Journal of Official Statistics, 19(3), 273–285.
Singer, E., Von Thurn, D. R., & Miller, E. R. (1995). Confidentiality assurances and response: A quantitative review of the experimental literature. Public Opinion Quarterly, 59(1), 66–77. https://doi.org/10.1086/269458
U.S. Department of Health and Human Services. (2018). Protection of human subjects (45 C.F.R. pt. 46).
Varnhagen, C. K., Gushta, M., Daniels, J., Peters, T. C., Parmar, N., Law, D., Hirsch, R., Sadler Takach, B., & Johnson, T. (2005). How informed is online informed consent? Ethics & Behavior, 15(1), 37–48. https://doi.org/10.1207/s15327019eb1501_3
World Medical Association. (2013). World Medical Association Declaration of Helsinki: Ethical principles for medical research involving human subjects. JAMA, 310(20), 2191–2194. https://doi.org/10.1001/jama.2013.281053